Introduction
This report summarizes financial information reported by Medicare Advantage organizations (MAOs) for calendar year (CY) 2025. This report includes financials for Medicare Advantage plan experience reported under Title XVIII Medicare line of business on the National Association of Insurance Commissioners (NAIC) annual statement. This is the seventh annual update of this report. The prior editions address annual experience dating back to CY 2019 and can be obtained from the Milliman website. The methodology used to generate this year’s report is substantially consistent with the prior year’s report. The Introduction section in prior editions includes additional background on Medicare Advantage product and financing, which some readers new to Medicare Advantage may find useful.
Enrollment in Medicare Advantage (MA) has continued to rise over the last several years. In 2025, 55% of Medicare-eligible beneficiaries opted into this government-sponsored program in which private health plans provide benefits to Medicare beneficiaries as an alternative to traditional fee-for-service (FFS) Medicare.1 For the health plans examined in this report, the composite reported underwriting margin for MAOs was negative in 2025, representing a slight decline from 2024 and the second consecutive year reflecting a composite underwriting loss. The lower reported financial experience is consistent with the higher trends and outlook presented by some of the leading national MA carriers during earnings calls in late 2025 and early 2026.2,3MAOs continued to face operational and financial pressures in 2025 from higher medical utilization, phase-in of the CMS-HCC version 28 risk adjustment model, and ongoing star rating regulatory changes. CY 2025 was also the first full-year implementation of the Inflation Reduction Act (IRA), which introduced new risk dynamics and shifted reinsurance liability.
This report summarizes the CY 2025 experience for selected financial metrics of organizations reporting MA experience under the Title XVIII Medicare line of business on the NAIC annual statement. We compiled this information from the reported annual statements.4 Individual reporting entities may be excluded from this report for the following reasons:
- Did not submit a health annual statement
- Reported less than $10 million in annual Medicare (Title XVIII) revenue
- Otherwise omitted from the NAIC database of health annual statements utilized for this report
The primary purpose of this report is to provide reference and benchmarking information for certain key financial metrics used in the analysis of MAO financial performance. This report summarizes the financial results on a composite basis for all reporting MAOs.
- Appendix 1 provides additional detail and stratifications of the financial metrics presented in this report.
- Appendix 2 provides the methodology and assumptions used in developing the metrics presented in this report.
Summary of CY 2025 financial results
The CY 2025 financial information analyzed for this report comprises information for 424 reporting entities across 46 states, excluding Alaska, Montana, Mississippi, and Wyoming, compared to 435 entities across 47 states in the prior year’s report. The above-mentioned states are not represented primarily because the reporting entities in these states were excluded based on the previously described filtering criteria. Of these 424 reporting entities, we identified 86 entities as provider-sponsored health plans (PSHPs), based on publicly available parent organization information and their status as provider entities. From this shortlist of 86 entities, we excluded large national PSHPs (such as Kaiser), as financial reporting for these plans is not representative of the subset being targeted for comparison purposes. We analyzed the financial performance of PSHPs separately from the traditional MAOs to identify any significant differences between the two entity types. These findings are outlined in later sections of this report. We retrieved the annual statements from an online NAIC database.
We compiled the financial data for the MAOs to produce outcomes of key financial metrics for various company groupings. We summarized the distribution of results to allow for user reference and benchmarking purposes. Unless otherwise stated, only companies with at least $10 million in MA revenue were used in this analysis.
The primary financial metrics we analyzed for this report include the medical loss ratio (MLR), administrative loss ratio (ALR), underwriting (UW) ratio, and risk-based capital (RBC) ratio. The selected metrics focus primarily on the income statement, except for the RBC ratio, which is a capital (or solvency) measure. Appendix 2 of this report documents the methodology and formulas behind these metrics.
Over the past five years, aggregate MA revenue (in dollars) has grown by 73%. Growth has been primarily driven by a year-to-year increase in Centers for Medicare and Medicaid Services (CMS) benchmark revenue, enrollment growth in the MA market from the increase in Medicare eligibles and higher MA penetration rates, and an increase through CY 2022 of the star ratings of the MAOs. However, the decrease in average star ratings—from 4.14 in CY 2023 to 3.95 in CY 2025—has somewhat offset these gains.5 Enrollment included in this report increased by 37% over the same five-year period, with a year-over-year increase of 4% growth rate this past year, dropping slightly from a 6% growth rate in the prior year.
Figure 1 summarizes the composite financial results of the 424 companies meeting the criteria selected for this study over the most recent five-year period. The companies in each year’s sample are not the same; however, the criteria used to select the companies are consistent from year to year. The total MA revenue base in CY 2025 represented over $470 billion (up from $423 billion last year), with underwriting losses of 0.8% (down from loss of 0.7% last year). The lower margins were consistent with information delivered in earnings calls and industry reports of the MA market. MAOs have reported pressures on margins due to elevated medical cost trends alongside competitive pressures around benefit offerings.6,7
Figure 1: Five-year historical financial results
Note: Values have been rounded.
We note the following observations on the MA market over the most recent five years:
- The composite UW ratio was negative for both CY 2024 and CY 2025, with CY 2025 being the lowest margin to date.
- The aggregate ALR over the last five years remained generally stable through CY 2024 at approximately 11%, with a decrease to 10% in CY 2025. This stability was driven by revenue growth outpacing administrative expenses, along with a shift in plan mix toward larger plans with lower reported ALRs.
- RBC ratios have generally decreased over the last five years, with CY 2023 being the only exception, primarily because authorized control level (ACL) has grown faster than total adjusted capital (TAC), placing downward pressure on aggregate RBC ratios.
- MLRs have increased each year beginning in CY 2023, with CY 2025 reaching the highest level observed in the past 10 years.
Please note that the MLR calculated throughout this report is the MLR formula as defined in Appendix 2. This is consistent with how MLR is reported on the statutory annual statement and not the formula used by CMS for MLR rebates, which includes adjustments for credibility, quality improvement activities, taxes and fees, or Part D reinsurance amounts.
While Figure 1 illustrates the overall changes in the underwriting results over the last five years, it is also important to understand how the underwriting results have varied across MAOs. Figure 2 illustrates the distribution of underwriting results in the MA market for each calendar year.
Figure 2: Distribution of underwriting results by year
The composite UW ratio decreased in CY 2025 to (-0.8%) and is a new five-year historical low after the previous historical low of -0.6% in CY 2024. The percentage of plans with a positive margin has increased compared to CY 2024 and CY 2023 but remained significantly lower than prior years. During CY 2021 and CY 2022, approximately 50% of the plans reported positive underwriting margins, decreasing to approximately 40% in CY 2023 and CY 2024. The composite UW ratio reported by the MAOs in CY 2025 represents an aggregate underwriting loss of approximately $3.5 billion in relation to the $470 billion of revenue.
For CY 2025, the 86 PSHPs meeting the criteria selected for this study showed underwriting losses of 3.3% in aggregate, compared to a 4.7% loss in CY 2024. Similar to prior years, a lack of scale, the potential to attract a higher acuity population, and conflicting incentives with the health system are some likely reasons why PSHPs tend to have higher loss ratios on average compared to non-PSHPs.
Figure 3 shows the distribution of MAOs (including PSHPs) within ranges of UW ratios specific to CY 2025, indicating that there were significantly more MAOs reporting losses (245 MAOs) compared to those reporting gains (179 MAOs). These results were consistent with CY 2024 but differed from CY 2023, when there was a relatively even split. Approximately half of the MAOs reported an underwriting margin within a range of plus or minus 5%. Plans with larger membership have been more profitable compared to smaller plans, which was generally consistent with CY 2024 reported experience; these results are illustrated in Figure 8 of Appendix 1. The underwriting ratio distribution for plans with greater than $1 billion in revenue was significantly different from the nationwide average, with 45% of those plans reporting gains. Figure 4 provides a view of the 86 PSHPs, which reflects a significantly different distribution: 38% of all PSHPs reported gains and about 13% reported losses of more than 20%.
Figure 3: CY 2025 underwriting ratio distribution
Figure 4: CY 2025 underwriting ratio distribution (PSHPS only)
We note the following observations on the MA market over the most recent five years:
Administrative cost analysis
Medicare Advantage-focused MAOs
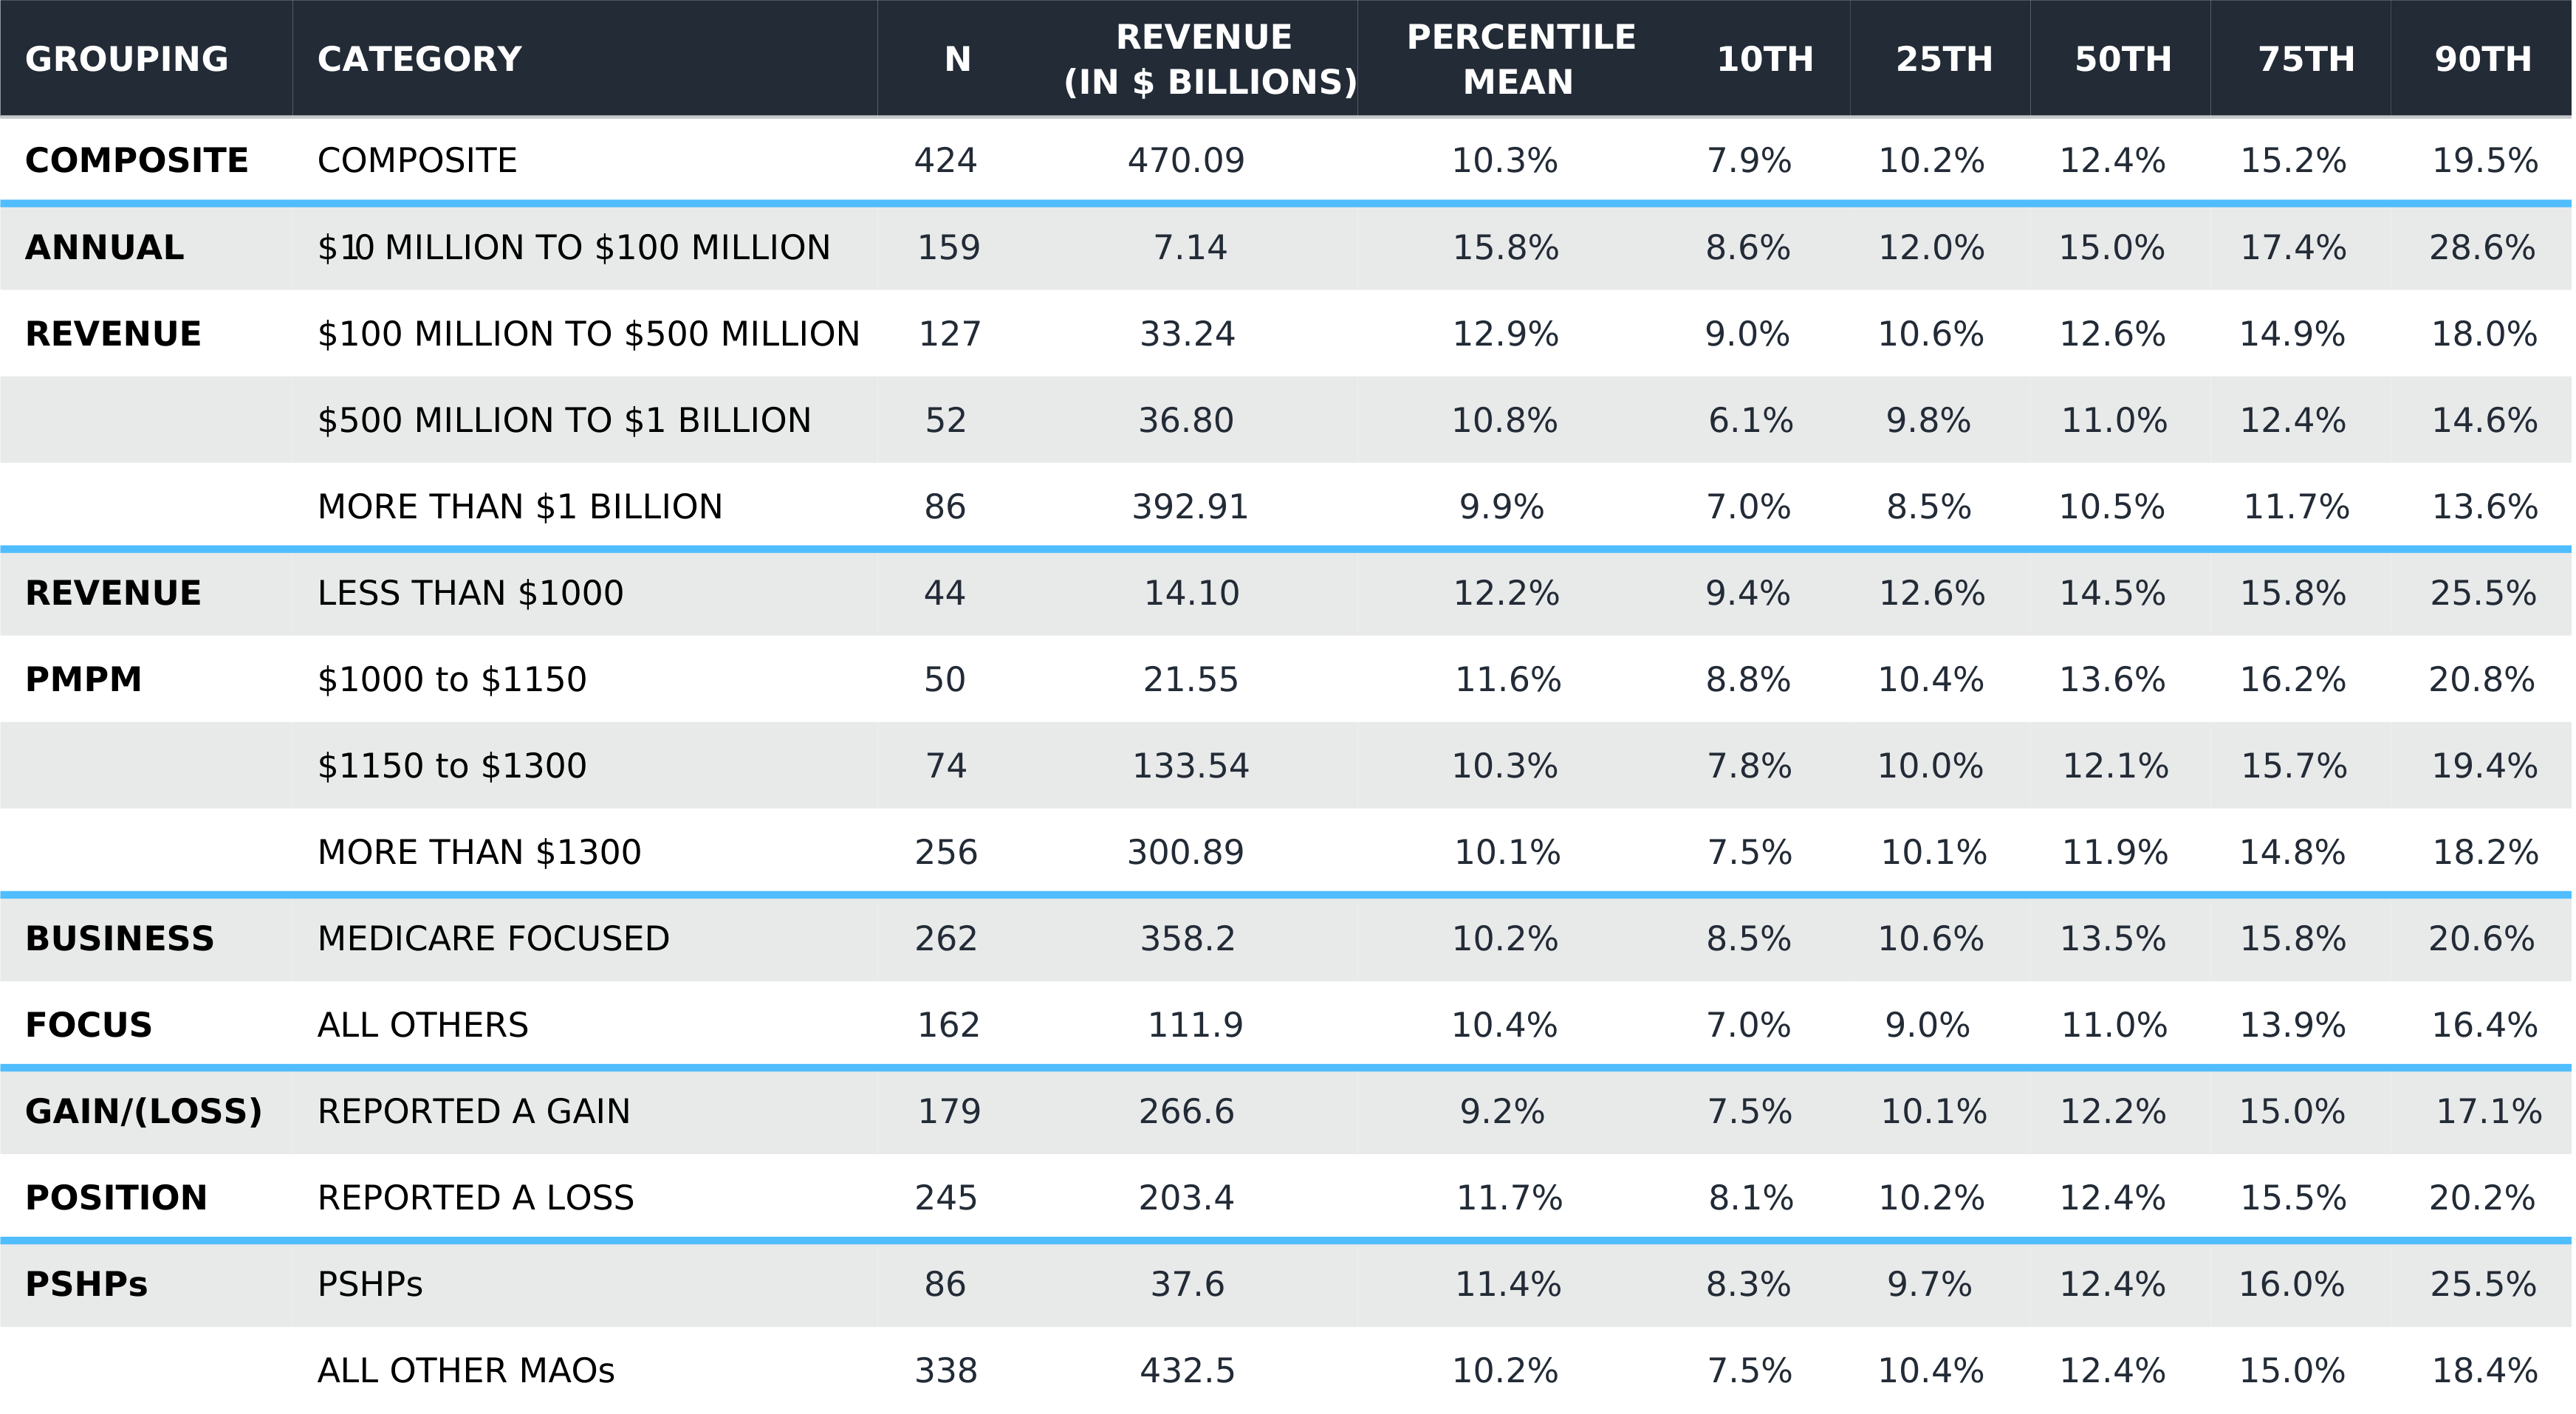
The results presented in this section of the report are limited to the 262 MAOs that are defined as MA-focused in the database used for this summary. The ALRs reported by the MA-focused MAOs were approximately 0.2% lower than the remaining 162 MAOs, which were defined as non-MA-focused. The 262 MA-focused MAOs account for over 76% of the MA revenue summarized for the purposes of this report, with an average ALR of 10.2%, a decrease of 0.6% compared to the prior year. The average ALR decrease appears to be driven by the growth in revenue outpacing administrative expenses, along with a shift toward larger plan carriers with lower ALRs. The following section summarizes the reported administrative costs for only the MA-focused MAOs to improve comparability, as organizations with broader lines of business may use differing administrative cost allocation methods that could affect direct comparisons.
Summary of results
The primary expense categories used in the Analysis of Operations by Line of Business page include the claim adjustment expenses (CAE) and general administrative expenses (GAE). The CAE and GAE categories are further stratified by additional subcategories of expenses in the Underwriting and Investment Exhibit Part 3 Analysis of Expenses page, which is the basis of the administrative expense categories illustrated below. Figure 5 summarizes the CY 2025 administrative expenses by quartile of ALR performance for the 262 companies with a MA focus.8 The administrative expenses are stratified by administrative cost categories.
Figure 5: Administrative loss ratio by quartile of ALR performance
In composite, MAOs grouped in the fourth quartile had higher administrative loss ratios across all expense types compared to MAOs grouped in the first, second, and third quartiles. Between the third and fourth quartiles, operating expenses and outsourcing accounted for most of the increase in administrative costs.
Figure 6 summarizes the administrative cost per member per month (PMPM) for the most recent five-year period for all 424 MAOs matching the inclusion criteria indicated in this report.
Figure 6: Administrative cost PMPM by year
Note: Values have been rounded.
Figure 6 illustrates a notable increase in the reported administrative cost on a PMPM basis from CY 2021 to CY 2023, followed by relative stabilization from CY 2023 to CY 2025. The median value shows an average annualized increase of 4.6%. The illustrated percentiles are less sensitive to outliers and changes in reported administrative expense for the largest health plans, as they reflect the overall distribution of administrative expenses by plan, not accounting for plan enrollment.
The PMPM increase over this five-year span was mostly attributable to general inflationary trends, as well as changes in the membership covered by the MAOs in this study, such as the increase in the number of beneficiaries in special needs plans (SNPs), which have higher claim and administrative costs. The range of administrative costs PMPMs faced over the years was likely attributable to a combination of drivers, such as additional operating expenses to support care management, coding and star rating initiatives, increased prevalence of SNPs (which require more intensive member care coordination), and/or other enrollment changes that can affect PMPMs.
Conclusion
Medicare Advantage remained popular and continued to grow in 2025. More than 55% of people eligible for Medicare in the United States enrolled in MA.9 Following last year’s pattern, MAOs saw increased pressure on their underwriting margins. The 2025 financials, similar to the prior year, showed that the Medicare Advantage margins decreased and the industry adapted to a tighter margin environment. Increases in claims trends, risk score dynamics, and regulatory changes were the major contributing factors. Looking forward, MAOs will need to balance member retention and maintain competitive benefit offerings. To succeed in the long term, MAOs will have to align operations around key areas, such as medical management, risk score accuracy under the new model, formulary management, and star performance metrics.
Limitations and data reliance
We compiled the results contained in this report using data and information obtained from the statutory annual statements for MAOs filed with the respective state insurance regulators. We retrieved the annual statements from an online NAIC database on July 9, 2026. In addition to the limiting criteria used to select companies in this report, certain MAOs may be omitted from this report because of the timing of annual statement submissions or their exclusions from the online database.
Milliman developed certain models to estimate the values included in this report. The intent of the models was to estimate the MAO financial results presented in this report. We reviewed the models, including their inputs, calculations, and outputs, for consistency, reasonableness, and appropriateness to the intended purpose and in compliance with generally accepted actuarial practice and relevant actuarial standards of practice (ASOP). The models rely on data and information as input to the models. We relied upon certain data and information for this purpose and accepted it without audit. To the extent that the data and information provided is not accurate or is not complete, the values provided in this correspondence may likewise be inaccurate or incomplete. Milliman’s data and information reliance includes the NAIC annual statement database. The models, including all input, calculations, and output, may not be appropriate for any other purpose.
This report is intended for informational purposes only. Milliman makes no representations or warranties regarding the contents of this report. Likewise, readers of this report are instructed that they are to place no reliance upon this report that would result in the creation of any duty or liability under any theory of law by Milliman or its employees to third parties.
The views expressed in this research paper are made by the authors and do not represent the opinions of Milliman, Inc. Other Milliman consultants may hold alternative views and reach different conclusions from those shown.
Qualifications
Guidelines issued by the American Academy of Actuaries require actuaries to include their professional qualifications in all actuarial communications. Shyam Kolli and Greg Sgrosso are members of the American Academy of Actuaries and meet the qualification standards for performing the analyses in this report.
Appendix 1: Financial metrics and MAO characteristics
In addition to the figures illustrated in the body of this report, we analyzed the financial metrics stratified by certain MAO characteristics to understand the potential impact these characteristics have on the reported financial results. The figures in Appendix 1 illustrate the following financial metrics and MAO characteristics:
Financial metrics
- Medical loss ratio
- Underwriting ratio
- Risk-based capital ratio
- Administrative loss ratio
MAO characteristics
- Annual Medicare revenue
- Annual Medicare revenue PMPM
- MAO type (Medicare-focused versus all other MAOs)
- Underwriting gain/loss
Figure 7: Medical loss ratio: CY 2025 results
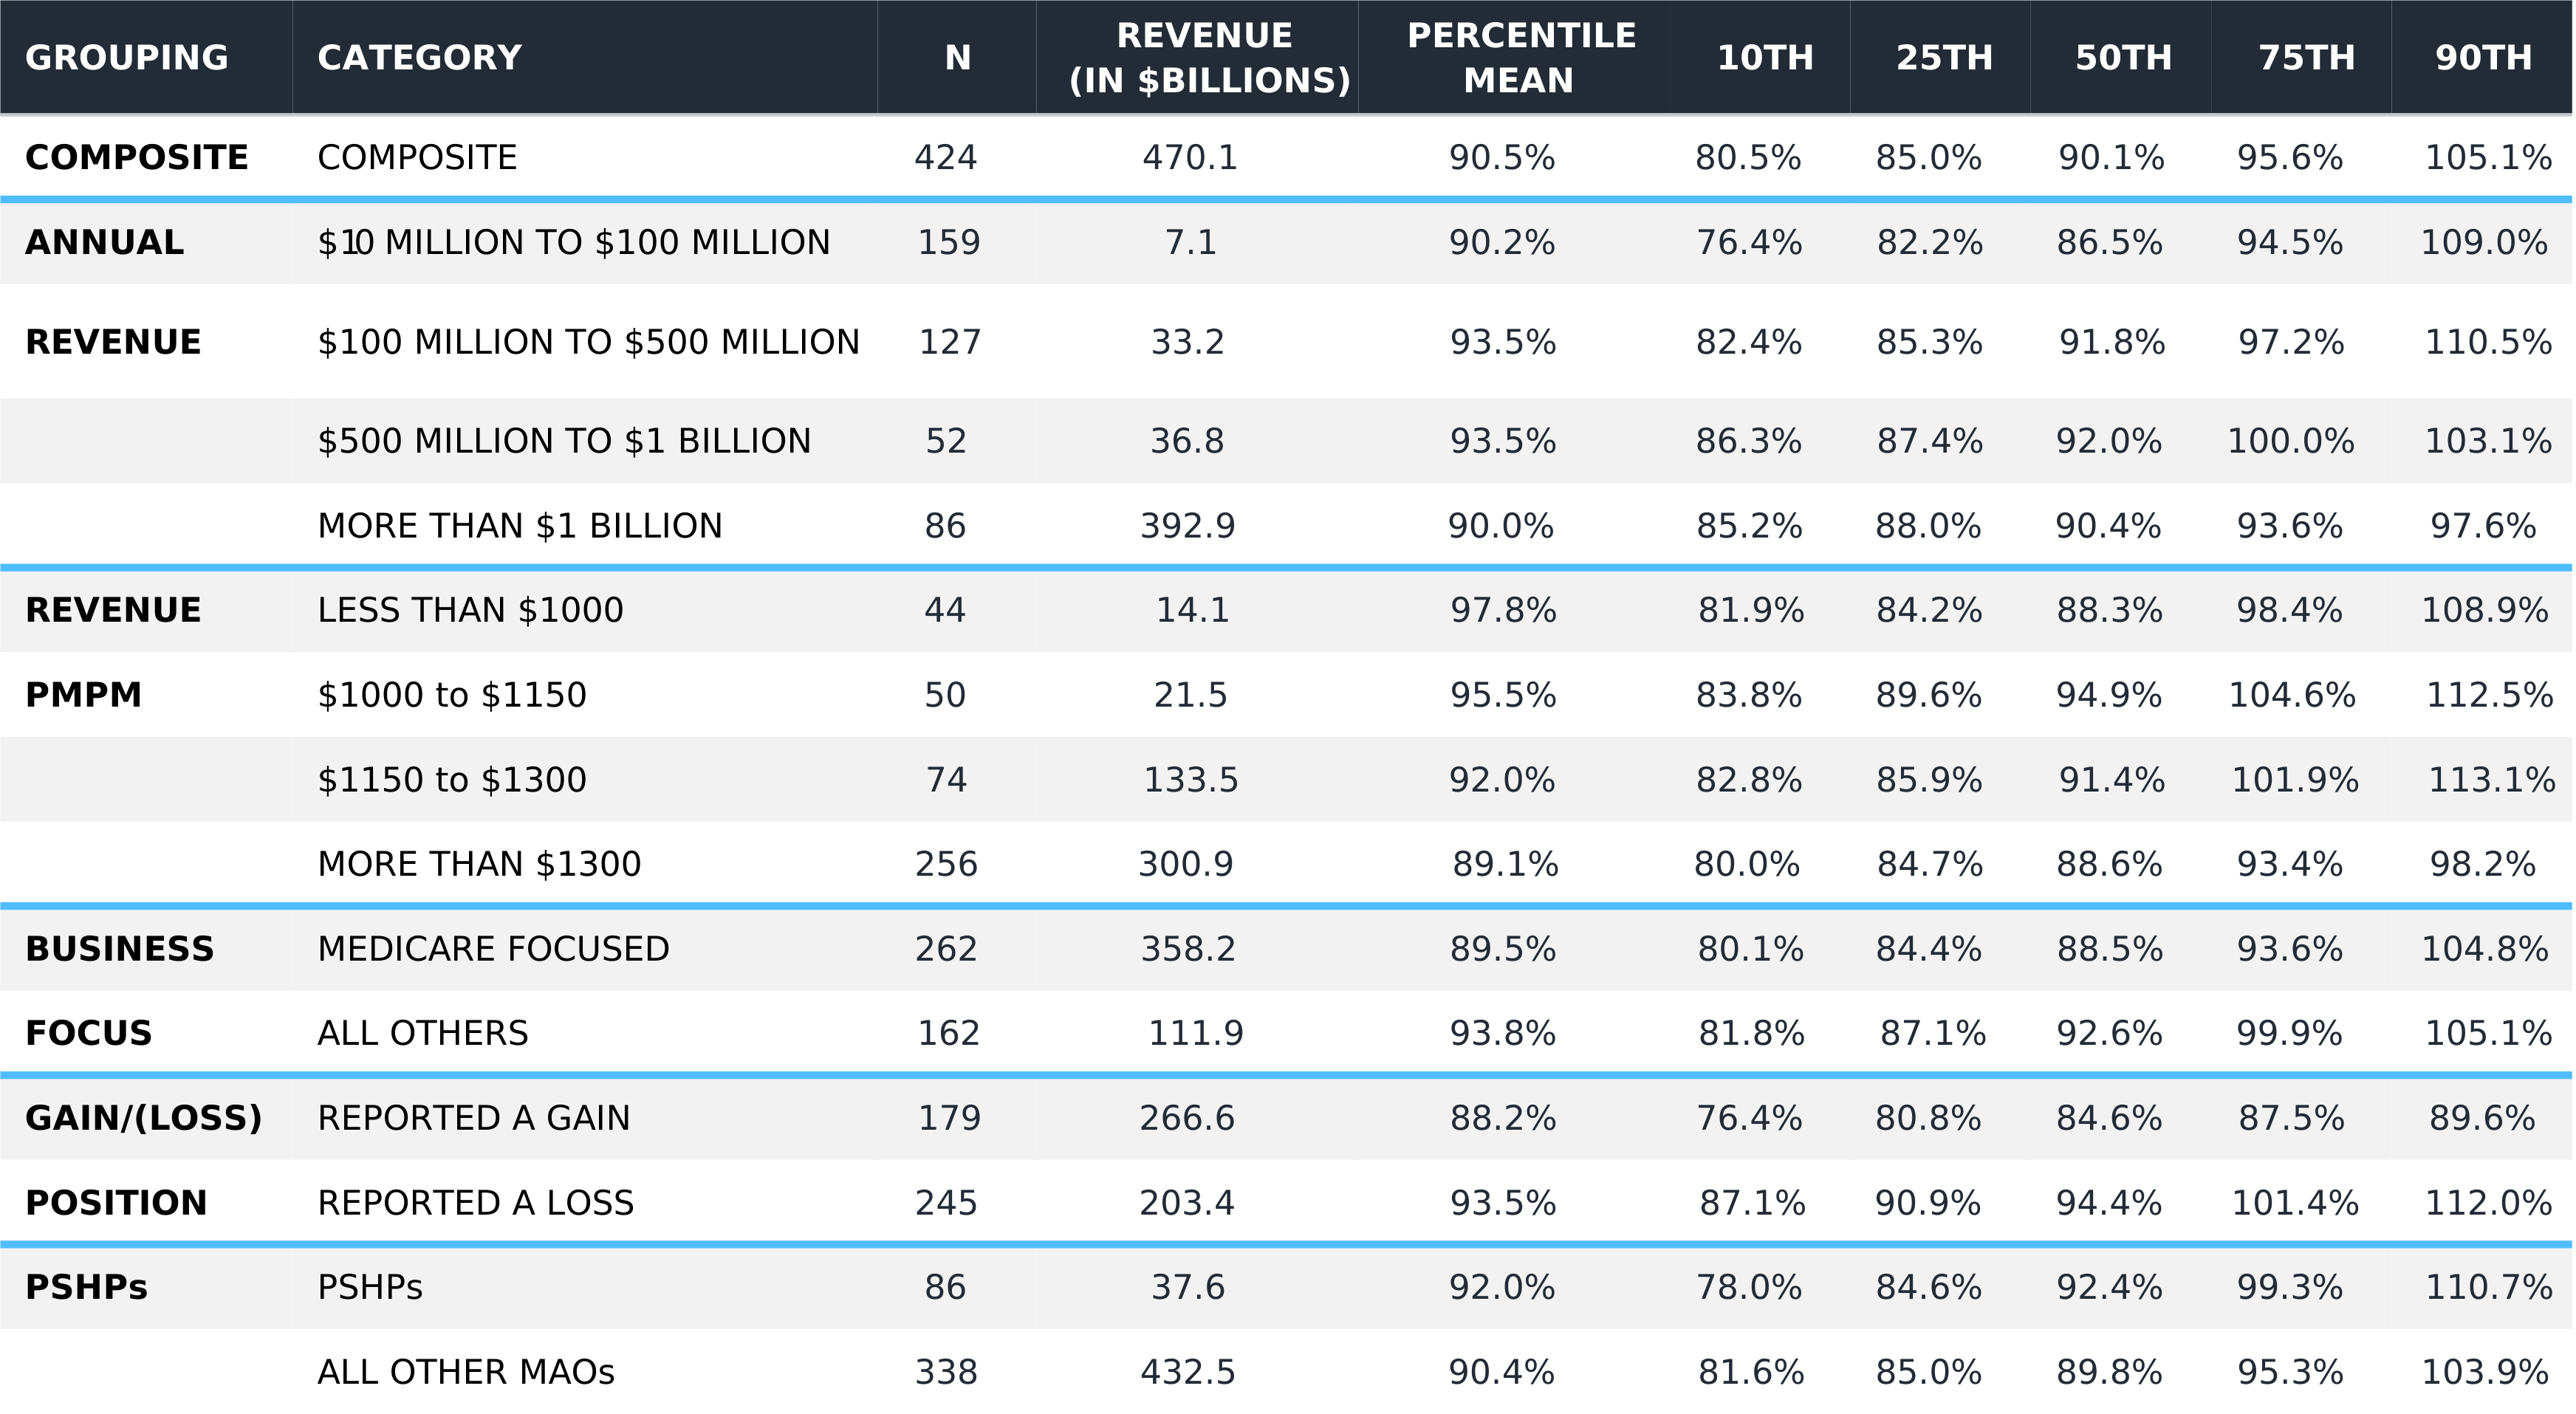
Figure 8: Underwriting ratio: CY 2025 results
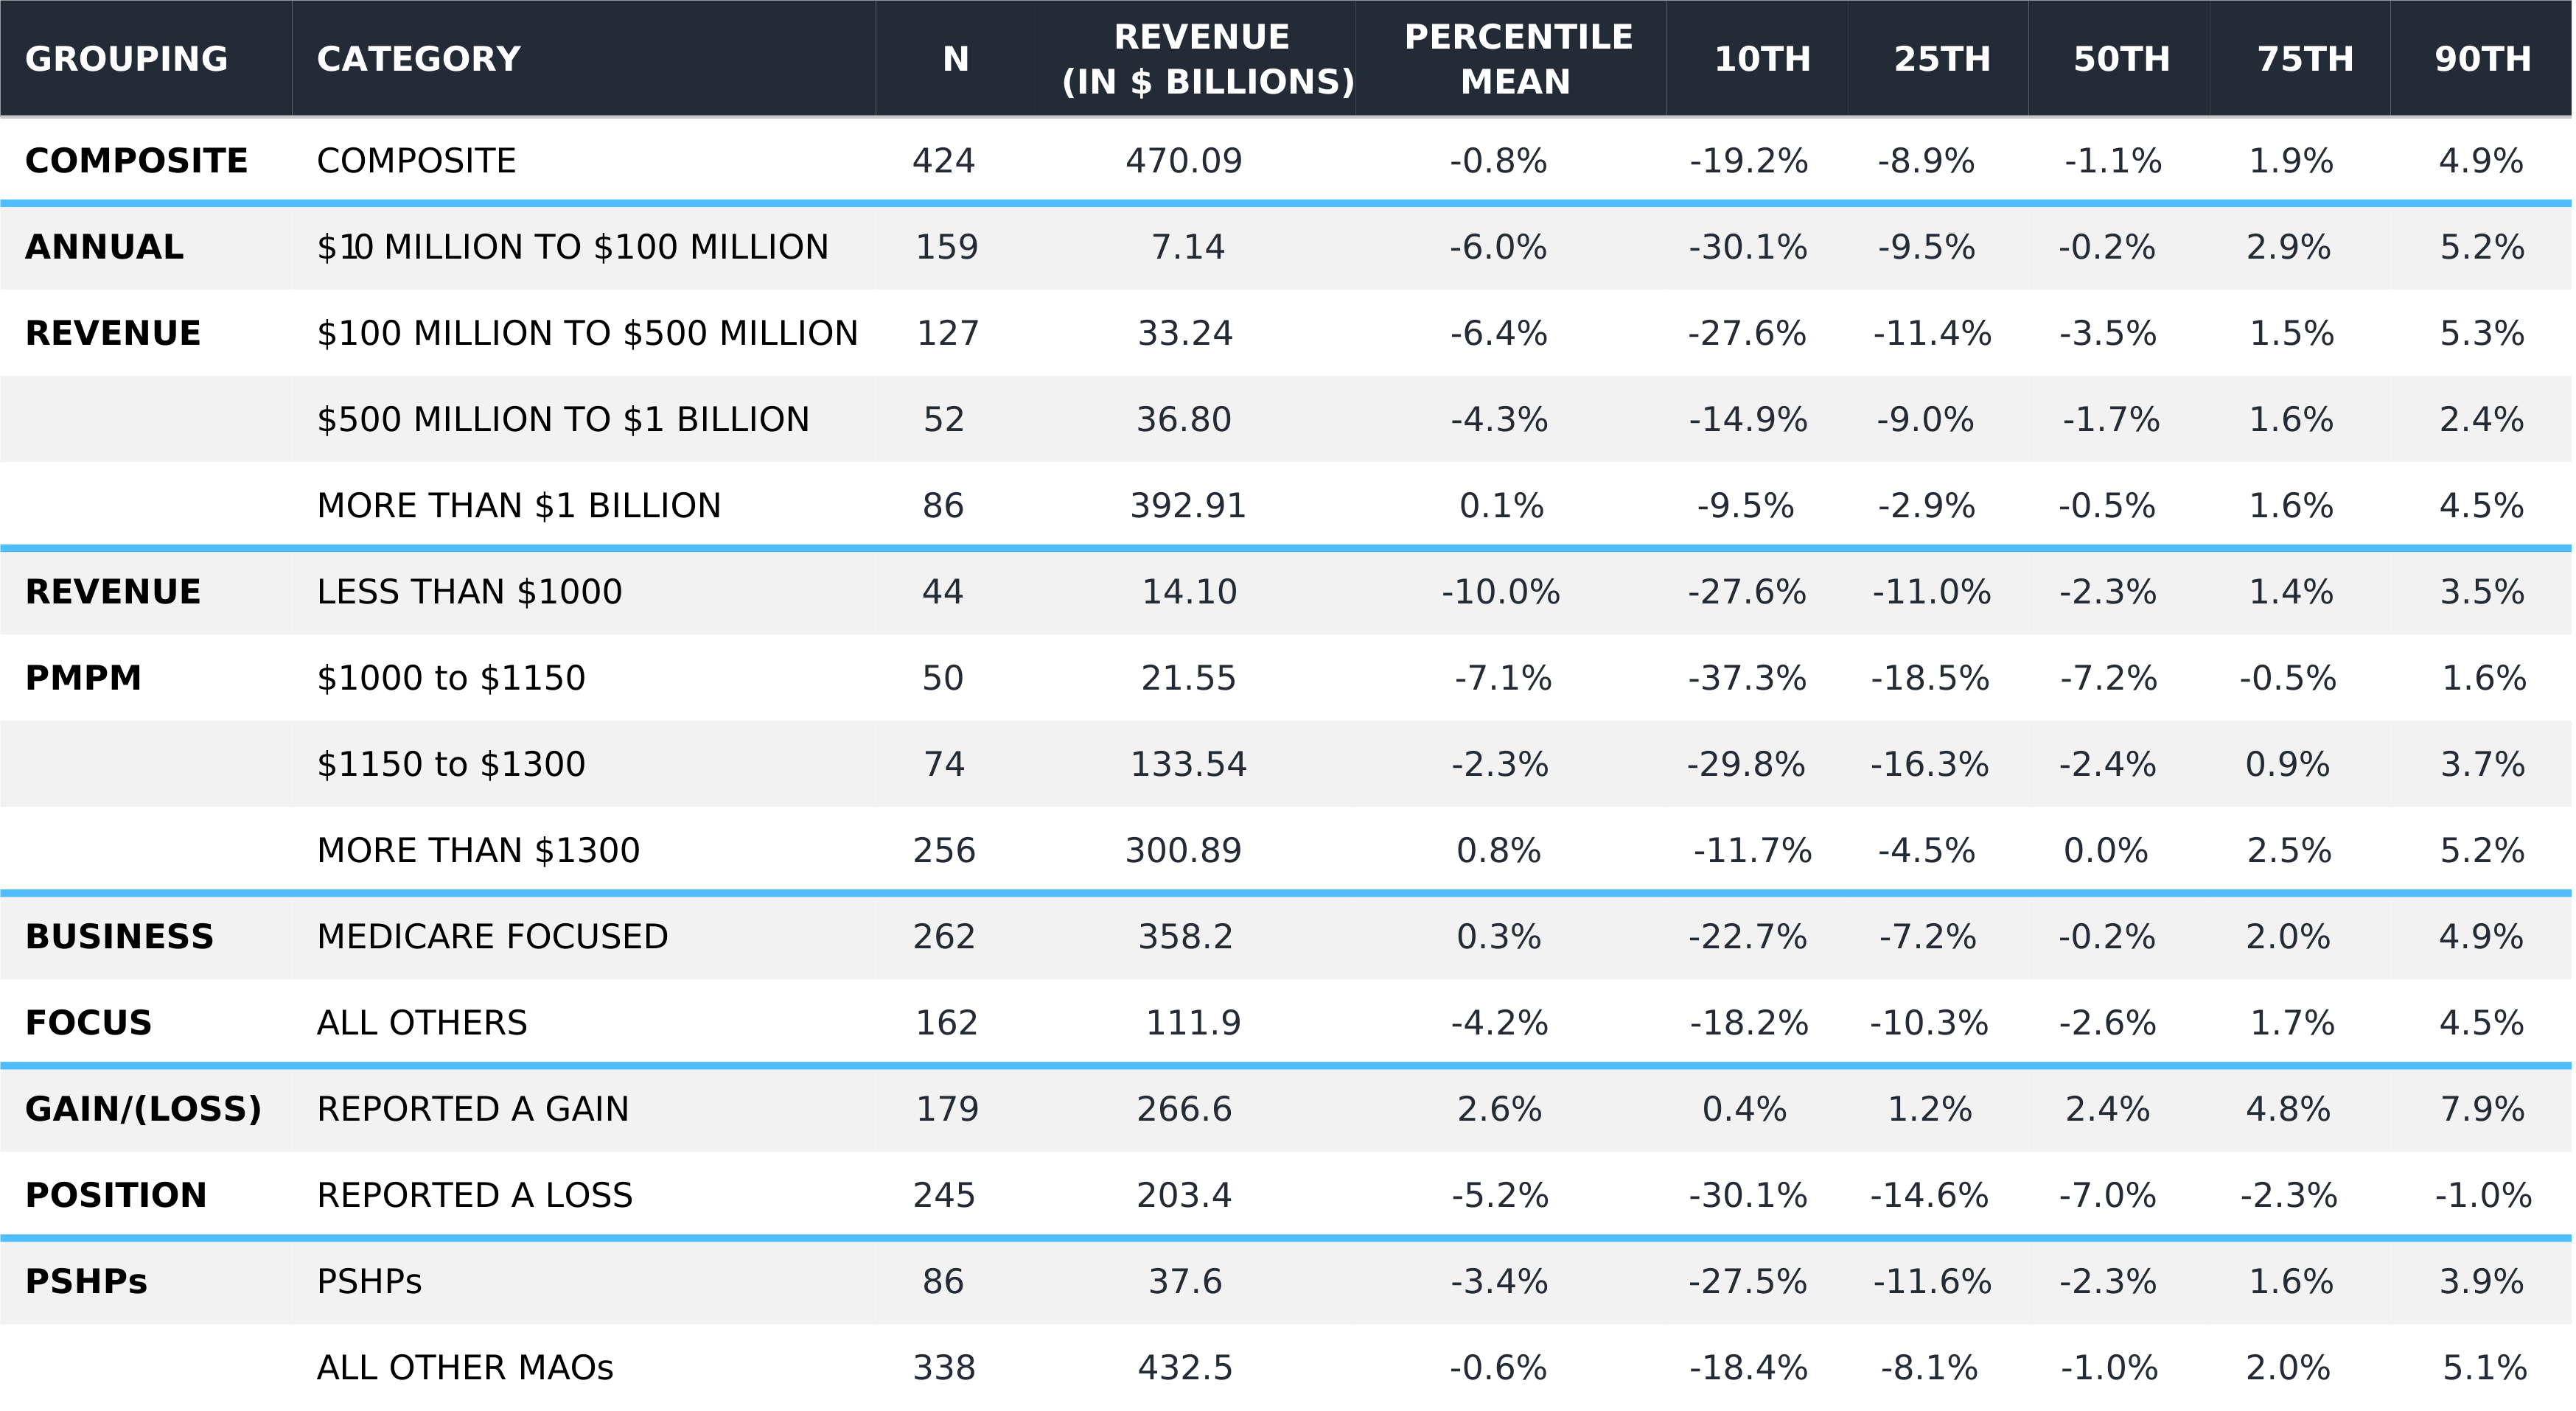
Figure 9: Risk-based capital ratio: CY 2025 results
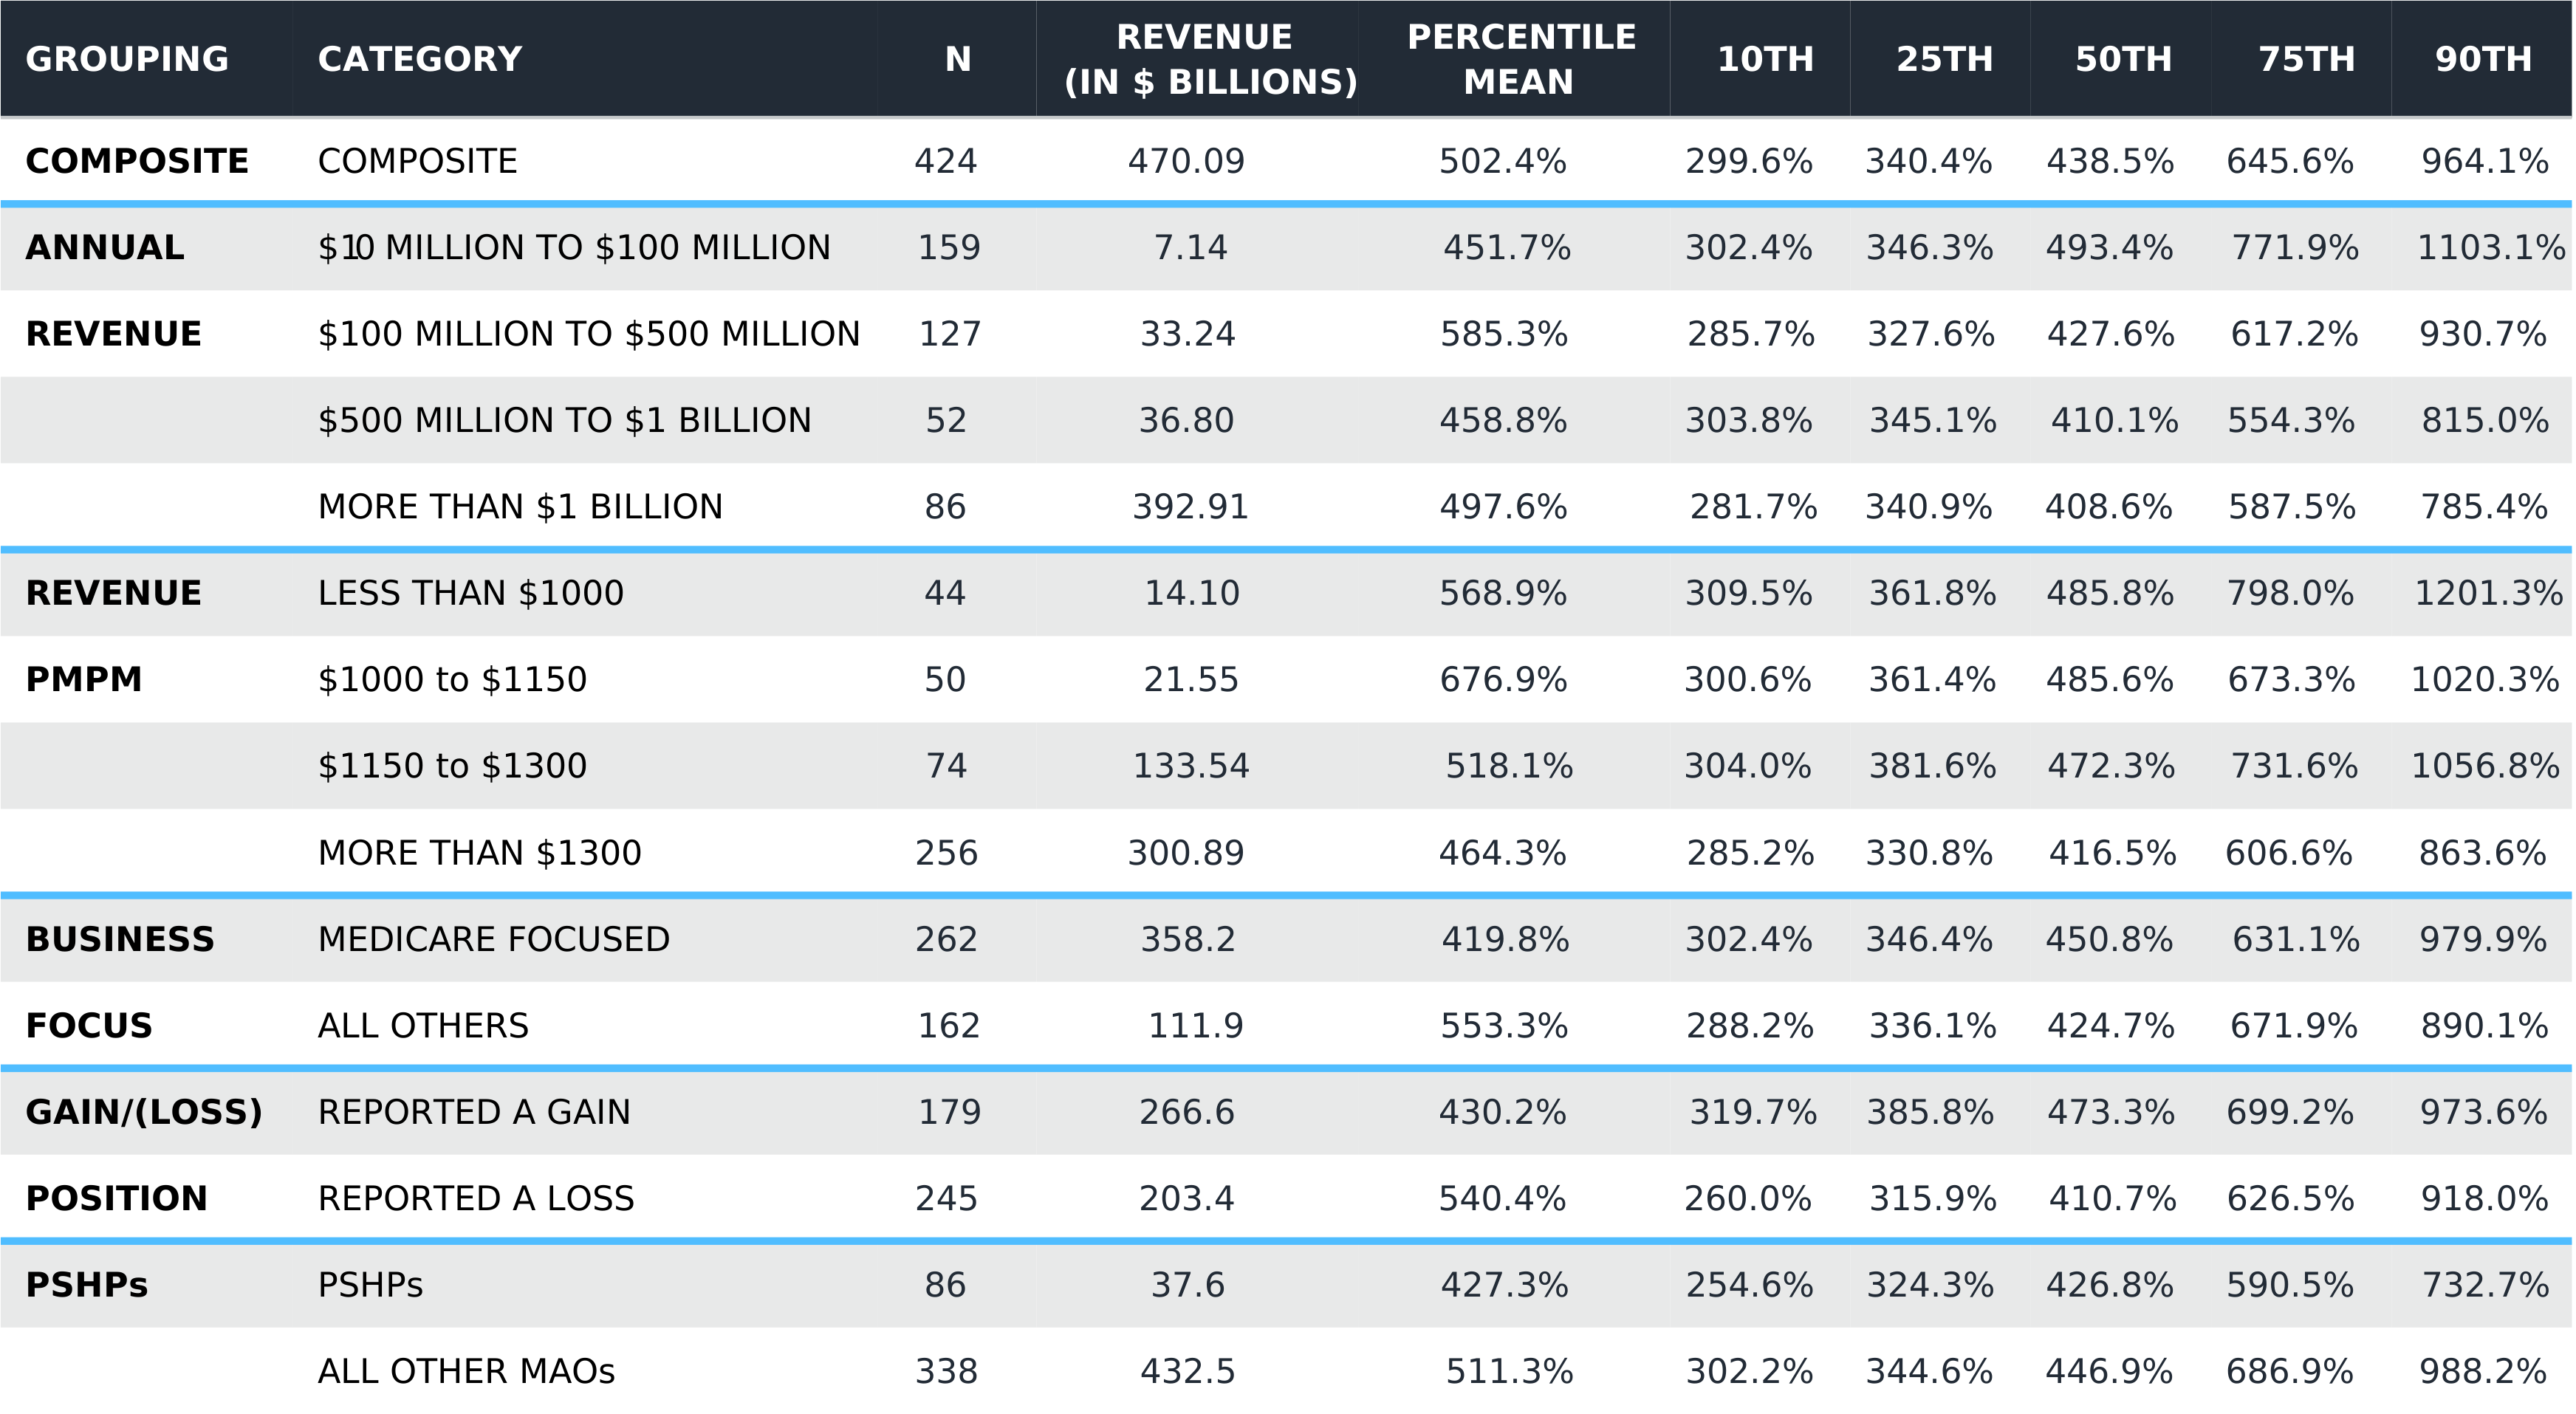
Figure 10: Administrative loss ratio: CY 2025 results
***Appendix 2: Definition of financial metrics***
The financial metrics calculated for the purposes of this report include medical loss ratio (MLR), administrative loss ratio (ALR), underwriting ratio (UW ratio), risk-based capital (RBC) ratio, and administrative cost PMPM. These selected metrics focus primarily on the income statement values of the financial statement except for the RBC ratio, which is a capital (or solvency) measure.
The financial metrics selected encompass five of the primary measures used by MAOs, regulators, and other stakeholders to evaluate the financial performance of a MAO. The metrics are defined in greater detail below.
Medical loss ratio (MLR)
MLR is a common financial metric used to report and benchmark the financial performance of a MAO. The MLR represents the proportion of revenue used by the MAO to fund claim expenses. The MLR is stated as a percentage, with claim expense in the numerator and revenue in the denominator.
In terms of the statutory annual statement, the MLR was defined as follows:
| MLR = | (TOTAL HOSPITAL AND MEDICAL EXPENSES + INCREASE IN RESERVES FOR A&H CONTRACTS) ÷ TOTAL REVENUE |
| WHERE: | TOTAL HOSPITAL AND MEDICAL EXPENSES: TITLE XVIII–MEDICARE (P.7, L.17, C.7) INCREASE IN RESERVES FOR ACCIDENT AND HEALTH (A&H) CONTRACTS: TITLE XVIII–MEDICARE (P.7, L.21, C.7) TOTAL REVENUE: TITLE XVIII–MEDICARE (P.7, L.7, C.7) |
As noted previously, the MA Part D program includes prospective payments for Low-Income Cost-Sharing Subsidy (LICS), Coverage Gap Discount Program (CGDP), and federal reinsurance. MAOs are not at risk for these programs. Neither the prospective payments nor the annual true-ups should be reported as revenue. The Part D program also includes a risk corridor program, where the MAOs and CMS share in favorable or unfavorable prescription drug experience relative to a bid target. The risk corridor payments or receivables should be included in revenue.
Actuaries and financial analysts use the MLR as a measure of premium adequacy. The target loss ratios (the claim cost included in the premium or capitation rate) vary by state and populations enrolled. Additionally, there may be reporting differences among MAOs as to what is classified as medical expense versus administrative expense.
As previously noted, the definition of MLR for the purposes of this report may not be consistent with other definitions.
Underwriting ratio
The UW ratio is the sum of the MLR and the ALR (defined below) subtracted from 100%. A positive UW ratio indicates an underwriting gain, while a negative UW ratio indicates a loss. This financial metric is used to report and benchmark the financial performance of an MAO in consideration of both medical and administrative expenses. The UW ratio represents the funding available after accounting for medical and administrative expenses. The UW ratio is stated as a percentage, with total underwriting gain or loss in the numerator and revenue in the denominator.
In terms of the statutory annual statement, the UW ratio was defined as follows:
| UW RATIO = | NET UNDERWRITING GAIN OR (LOSS) ÷ TOTAL REVENUE |
| WHERE: | NET UNDERWRITING GAIN OR (LOSS): TITLE XVIII–MEDICARE (P.7, L.24, C.7) TOTAL REVENUE: TITLE XVIII–MEDICARE (P.7, L.7, C.7) |
The UW ratio is focused on the income from operations and excludes consideration of investment income and income taxes. The UW ratio requires interpretation and considerations similar in nature to the MLR and ALR metrics.
Risk-based capital ratio (RBC ratio)
The RBC ratio is a financial metric used by many insurance regulators to monitor the financial health or solvency of MAOs. The RBC ratio represents the proportion of the required minimum capital that is held by the MAO as of a specific date (the end of the financial reporting period). The RBC ratio is stated as a percentage or a ratio, with total adjusted capital (TAC) in the numerator and authorized control level (ACL) in the denominator.
The NAIC prescribes a specific formula to develop both the TAC and the ACL. Further, the MAO is subjected to various action levels based on the resulting RBC ratio, as follows:
- Company action level (TAC is between 150% and 200% of the ACL RBC)
- Regulatory action level (TAC is between 100% and 150% of the ACL RBC)
- Authorized control level (TAC is between 70% and 100% of the ACL RBC)
- Mandatory control level (TAC is less than 70% of the ACL RBC)
In terms of the statutory annual statement, the RBC ratio was defined as follows:
| RBC RATIO = | TOTAL ADJUSTED CAPITAL ÷ AUTHORIZED CONTROL LEVEL |
| WHERE: | TOTAL ADJUSTED CAPITAL: TOTAL ADJUSTED CAPITAL–CURRENT YEAR (P.28, L.14, C.1) AUTHORIZED CONTROL LEVEL: AUTHORIZED CONTROL LEVEL–CURRENT YEAR (P.28, L.15, C.1) |
Note: The RBC ratio is not unique to the MA line of business, as it is calculated at the company level. Therefore, companies reporting non-Medicare business will reflect composite RBC ratios for all lines of business within the reported legal entity.
Administrative loss ratio (ALR)
ALR is also a common financial metric used to report and benchmark the financial performance of a MAO. The ALR represents the proportion of revenue that was used by the MAO to fund administrative expenses. The ALR is stated as a percentage, with administrative expense in the numerator and revenue in the denominator.
In terms of the statutory annual statement, the ALR was defined as follows:
| ALR = | (CLAIM ADJUSTMENT EXPENSES + GENERAL ADMINISTRATIVE EXPENSES) ÷ TOTAL REVENUE |
| WHERE: | CLAIM ADJUSTMENT EXPENSES: TITLE XVIII–MEDICARE (P.7, L.19, C.7) GENERAL ADMINISTRATIVE EXPENSES: TITLE XVIII–MEDICARE (P.7, L.20, C.7) TOTAL REVENUE: TITLE XVIII–MEDICARE (P.7, L.7, C.7) |
The ALR requires interpretation and considerations similar in nature to the MLR metric outlined above, most notably impacted by the state and federal taxes levied on MAOs across the different states.
Administrative cost PMPM
The administrative cost PMPM is the second metric for analyzing administrative expenses because of the fixed cost nature of certain components of the administrative expense. The administrative cost PMPM was defined as follows:
| ADMIN PMPM = | (CLAIM ADJUSTMENT EXPENSES + GENERAL ADMINISTRATIVE EXPENSES) ÷ CURRENT YEAR MEMBER MONTHS |
| WHERE: | CLAIM ADJUSTMENT EXPENSES: TITLE XVIII–MEDICARE (P.7, L.19, C.7) GENERAL ADMINISTRATIVE EXPENSES: TITLE XVIII–MEDICARE (P.7, L.20, C.7) CURRENT YEAR MEMBER MONTHS: TITLE XVIII-MEDICARE (P.30 GT, L.6, C.8) |
Administrative expense categories
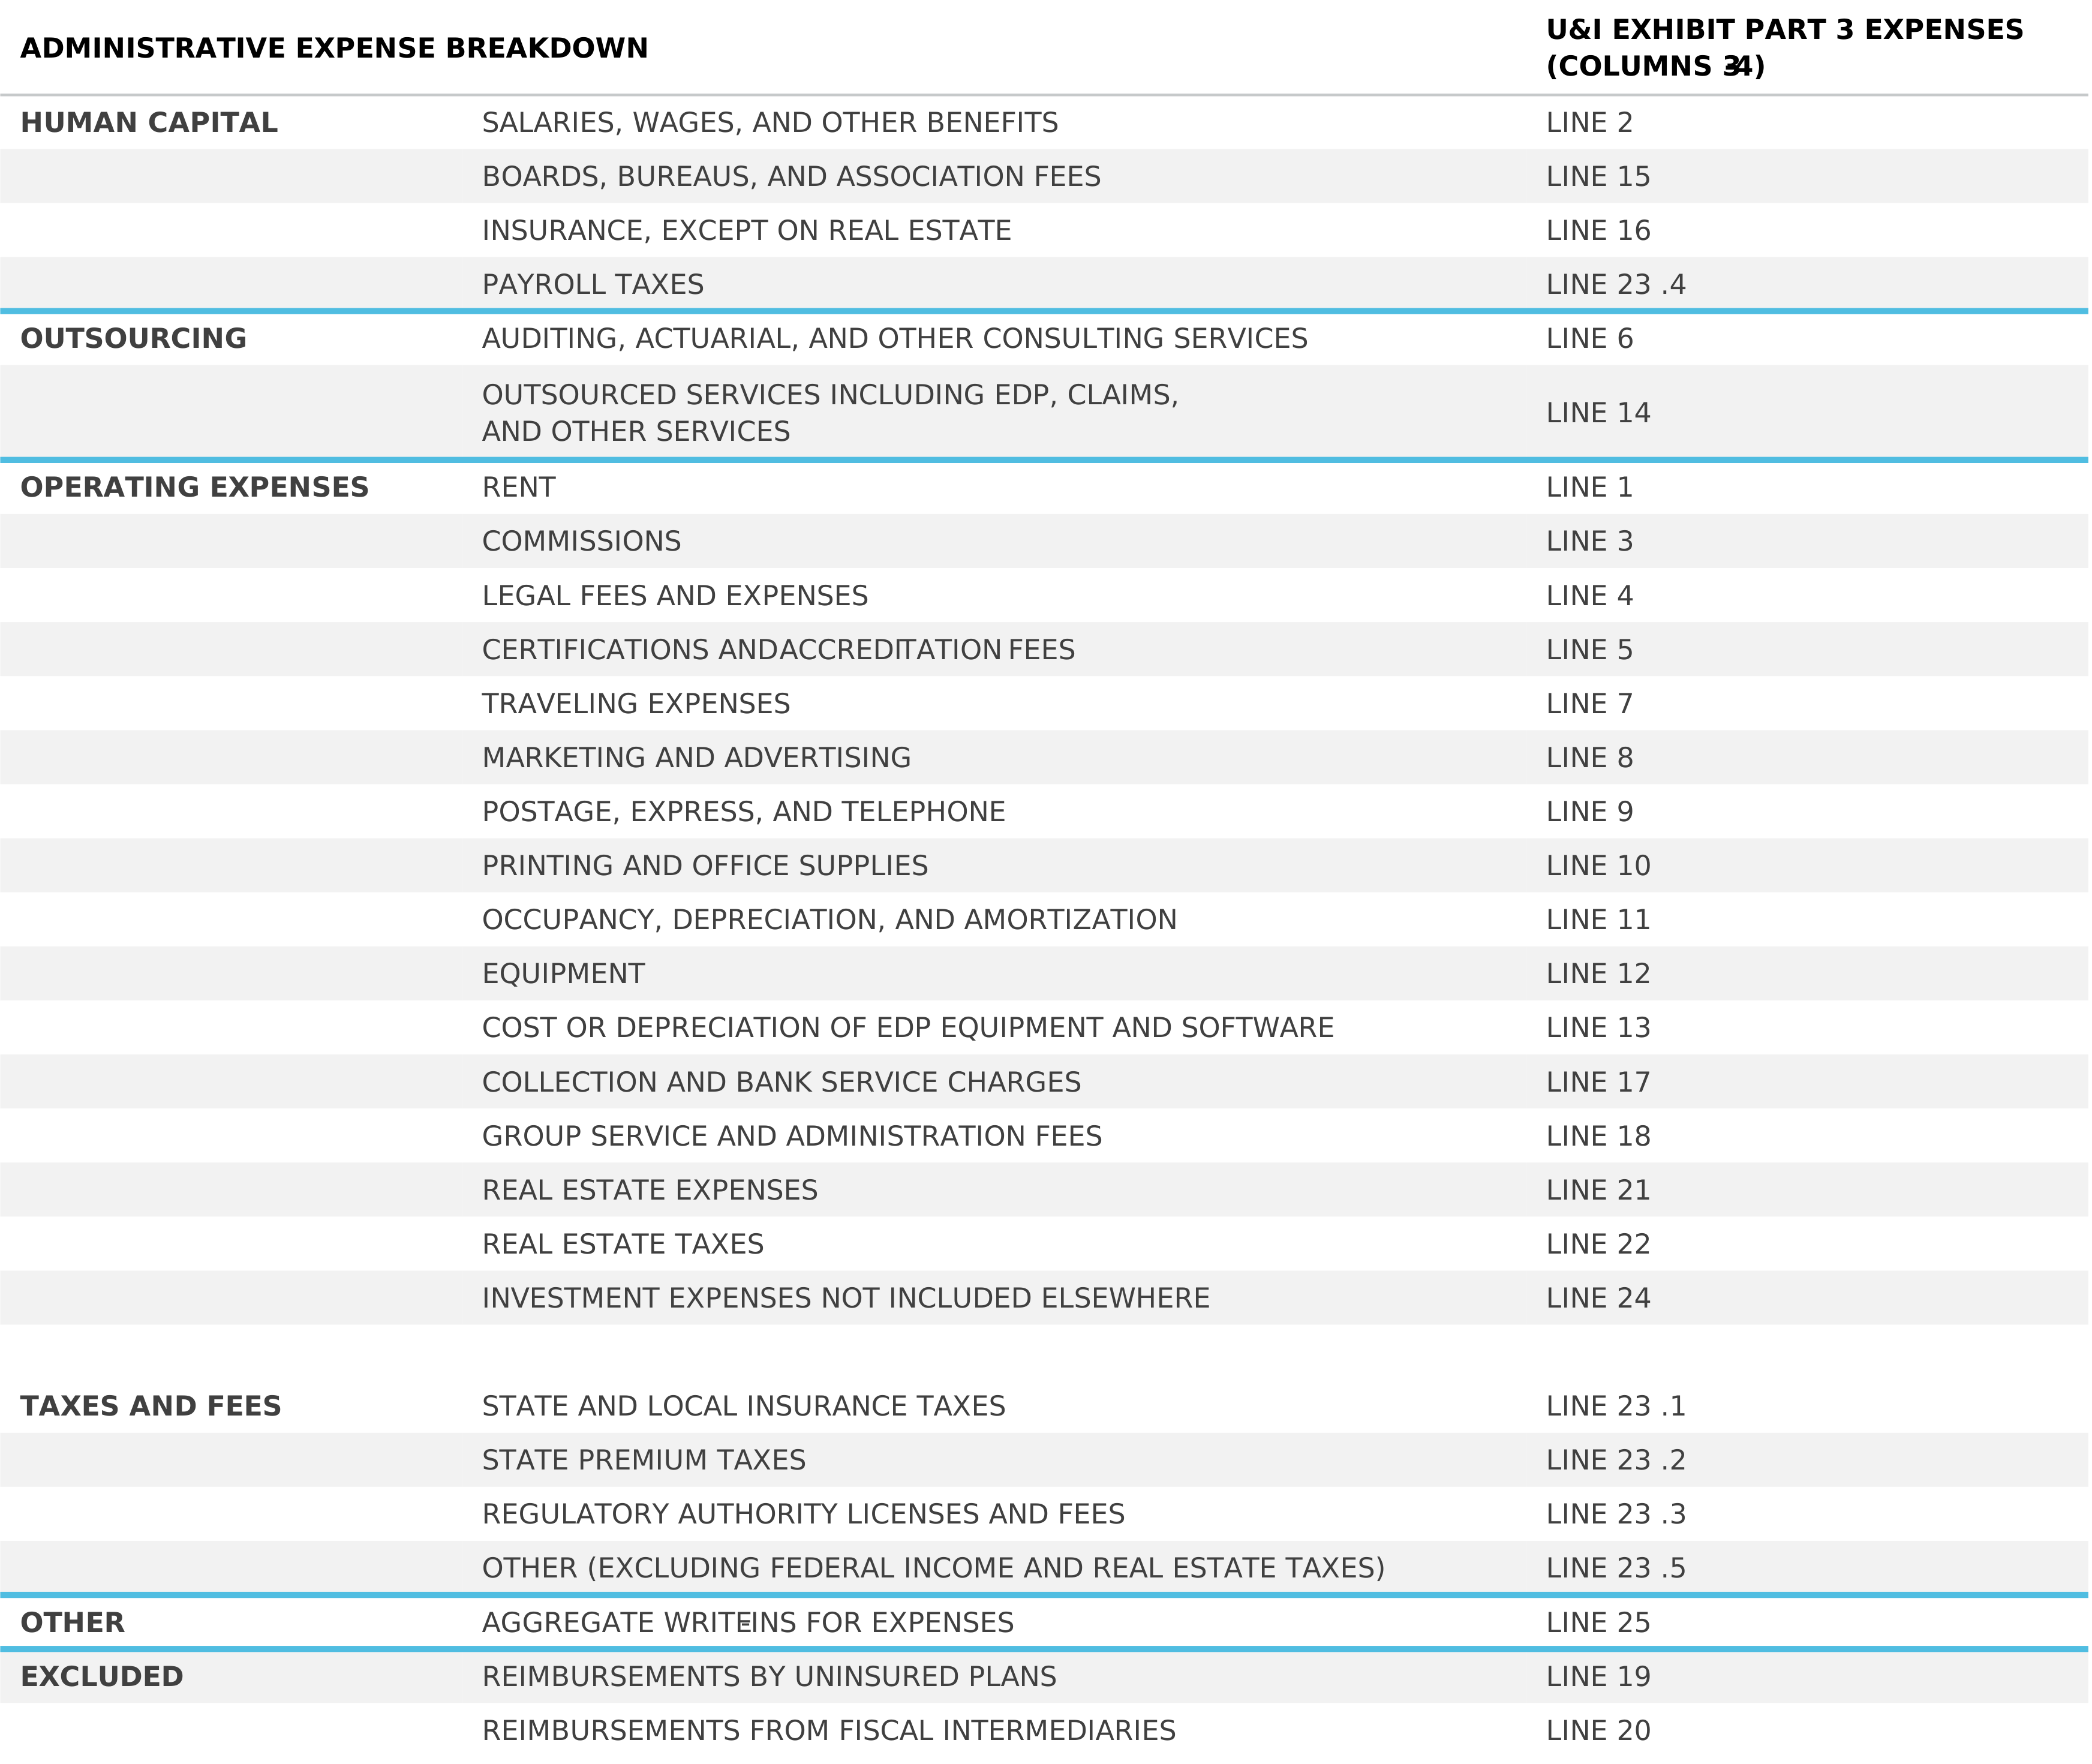
The administrative expenses reported on the Underwriting and Investment Exhibit Part 3 Analysis of Expenses page are categorized into 25 specific line items. We grouped these line items into five administrative expense categories to better illustrate the components of administrative cost incurred by the MAOs. The subcategories were selected to be intuitive groupings, as well as meaningful with respect to their relative magnitudes. The following descriptions outline each administrative expense category:
- Human capital: Administrative costs associated with the employment of MAO staff.
- Outsourcing: Administrative costs associated with functions outsourced to a third party.
- Operating expenses: Administrative costs associated with the day-to-day costs of running the MAO.
- Taxes and fees: Administrative costs associated with taxes and fees incurred by the MAO. We assigned payroll taxes to the human capital category. We assigned real estate taxes to the operating expenses category.
- Other expenses: Administrative costs for aggregate write-ins.
Figure 11: Administrative category definition
About the authors
Sean MacQuarrie is an actuarial analyst at Milliman. Mr. MacQuarrie joined Milliman in 2023 and primarily works on life science projects and Medicare Advantage pricing.
Phil Ellenberg is a healthcare consultant at Milliman. Mr. Ellenberg joined Milliman in 2016 and specializes in predictive analytics and business intelligence.
Shyam Kolli is a principal and consulting actuary at Milliman and is a fellow of the Society of Actuaries and a member of the American Academy of Actuaries. Mr. Kolli joined Milliman in 2010 and has 20 years of healthcare-related actuarial experience.
Greg Sgrosso is a principal and consulting actuary at Milliman and is a fellow of the Society of Actuaries and a member of the American Academy of Actuaries. Mr. Sgrosso joined Milliman in 2002 and has 24 years of actuarial healthcare-related experience.
Acknowledgments
The authors further acknowledge Chris Pettit, FSA, MAAA, principal and consulting actuary, and Luis Maldonado, FSA, MAAA, principal and consulting actuary, at Milliman, for their peer review and comments during the writing of this report.
1 Freed, M., Fuglesten Biniek, J., Damico, A., Ochieng, N., & Neuman, T. (June 5, 2026). Medicare Advantage in 2026: Enrollment update and key trends. Kaiser Family Foundation. Retrieved August 15, 2026, from https://www.kff.org/medicare/medicare-advantage-enrollment-update-and-key-trends/.
2 UnitedHealth Group. (January 27, 2026). UnitedHealth Group reports 2025 results and issues 2026 outlook. Retrieved October 28, 2026, from https://www.unitedhealthgroup.com/content/dam/UHG/PDF/investors/2025/unh-reports-2025-results-and-issues-2026-outlook.pdf.
3 Humana. (July 29, 2026). Q2 2026 earnings call corrected transcript. FactSet CallStreet. Retrieved October 28, 2026, from https://humana.gcs-web.com/static-files/d10ba81b-24f4-4855-bc93-1f1a104daac2.
4 National Association of Insurance Commissioners. Annual Statement Database, as delivered by S&P Global, Inc, all rights reserved.
5 Average member weighted star ratings by year for 2023 and 2025 were calculated from the following source: Centers for Medicare and Medicaid Services. (November 18, 2025). 2026 Medicare Advantage and Part D star ratings. Retrieved October 28, 2026, from https://www.cms.gov/files/document/2026-star-ratings-fact-sheet.pdf.
6 UnitedHealth Group. (January 27, 2026). UnitedHealth Group reports 2025 results and issues 2026 outlook. Retrieved October 28, 2026, from https://www.unitedhealthgroup.com/content/dam/UHG/PDF/investors/2025/unh-reports-2025-results-and-issues-2026-outlook.pdf.
7 Humana. (July 29, 2026). Q2 2026 earnings call corrected transcript. FactSet CallStreet. Retrieved October 28, 2026, from https://humana.gcs-web.com/static-files/d10ba81b-24f4-4855-bc93-1f1a104daac2.
8 A quartile is a cut point dividing the number of data points in a data set into four parts, or quarters, of roughly equal size.
9 Freed, M., Fuglesten Biniek, J., Damico, A., Ochieng, N., & Neuman, T. (June 5, 2026). Medicare Advantage in 2026: Enrollment update and key trends. Kaiser Family Foundation. Retrieved August 15, 2026, from https://www.kff.org/medicare/medicare-advantage-enrollment-update-and-key-trends/.